Tuesday, 18 May 2021

🟢 Οι αριθμοί της Φρίκης. Και της Απάτης


🟢 Από τότε που άρχισαν οι εμβολιασμοί στην Κύπρο ΕΝΑ ΤΡΙΤΟ ΤΩΝ ΝΕΚΡΩΝ με κορωνοϊό είναι ΕΜΒΟΛΙΑΣΜΕΝΑ άτομα. Αυτό τεκμηριώθηκε από τις ίδιες τις Αρχές με τους αριθμούς που δημοσιεύουν, και επιβεβαιώθηκε μες το πρόσφατο δεκαήμερο τόσο από δημοσιεύματα του καθεστωτικού Τύπου/ΜΜΕ, όσο και από κύπριους επιστήμονες.


🟢 Οι Ιατρικές και Κρατικές Αρχές μαζί με τα συνένοχα ΜΜΕ έχουν φρίξει με αυτή την παταγώδη αποτυχία: η απελπισία τους, και οι ασήκωτες - ένοχες! - ευθύνες των, τους έσπρωξαν αυτή την εβδομάδα στο να ΑΠΑΓΟΡΕΥΣΟΥΝ την δημοσιοποίηση των αριθμών των ΝΕΚΡΩΝ ΕΜΒΟΛΙΑΣΜΕΝΩΝ!


🟢 Και δεν είναι μόνο αυτά. Όπως θα δείτε πιο κάτω στην ανάλυση της κατάστασης, τα πράγματα είναι πολύ χειρότερα από ό,τι φαίνονται εκ πρώτης όψεως. Ας δούμε πρώτα τις πηγές ενημέρωσης - εδώ μπορείτε να επιβεβαιώσετε του λόγου το αληθές:

■ Κάτω από το Κεφάλαιο "Κρούσματα" μπορείτε να δείτε όλες τις σχετικές ανακοινώσεις του Γραφείου Τύπου και Πληροφοριών:
https://www.pio.gov.cy/coronavirus/categories/press

Τα ΜΜΕ αθροίζουν τους αριθμούς που ανακοινώνονται πιο πάνω και κάθε τόσο δημοσιεύουν τεκμηριωμένα συναθροίσματα:

■ 1 στους 3 που πέθαναν μεταξύ 24/3-9/5 είχε ιστορικό εμβολιασμού
https://simerini.sigmalive.com/article/2021/5/14/1-stous-3-pou-pethanan-metaxu-243-95-eikhe-istoriko-emboliasmou

■ Γιατί έφυγαν από τη ζωή 19 συνάνθρωποι μας ενώ εμβολιάστηκαν κατά του Covid
https://www.alphanews.live/cyprus/giati-efygan-apo-ti-zoi-19-synanthropoi-mas-eno-emboliastikan-kata-toy-covid

Παρόμοια δημοσιεύματα με τους επί μέρους (όχι συνολικούς) θανάτους συμπεριλαμβάνονται πιο κάτω στις Σημειώσεις, [1], [2].


🟢 Ανάλυση: Μέρος Α ~ Η επιστημονική τεκμηρίωση
Αυτό το δεκαήμερο που κορυφώθηκαν οι θάνατοι ΕΜΒΟΛΙΑΣΘΕΝΤΩΝ ατόμων με κορωνοϊό, συμπληρώθηκε ο εμβολιασμός περίπου 30% (ένα τρίτο) του πληθυσμού.

Από τότε που άρχισαν οι εμβολιασμοί στην Κύπρο, μέχρι και το τελευταίο δεκαήμερο είχαν πεθάνει περίπου 75 άτομα, εκ των οποίων περίπου 30% (ένα τρίτο) ήταν ΕΜΒΟΛΙΑΣΘΕΝΤΕΣ. Το λέμε και διαφορετικά για να γίνει κατανοητό: ΕΝΑ ΤΡΙΤΟ ΤΩΝ ΝΕΚΡΩΝ ήταν ΕΜΒΟΛΙΑΣΘΕΝΤΕΣ.

Ο φαρμακοποιός Σώτος Χριστοδούλου που παρακολουθεί στενά την κατάσταση αναλύοντας σχεδόν καθημερινά τους επίσημους αριθμούς που δημοσιεύουν οι Αρχές, στην αρχή του πρόσφατου δεκαήμερου φρίκης δήλωσε τα εξής - ήταν ο πρώτος με επιστημονική κατάρτηση που σήμανε συναγερμό για το θέμα:

■ "Μέχρι στιγμής έχουν πάρει την πρώτη δόση εμβολίου το 27,9% του πληθυσμού και έχουν ολοκληρώσει το εμβολιαστικό σχήμα το 9.5% του πληθυσμού.

Αν λοιπόν το εμβόλιο παρέχει έστω και την παραμικρή προστασία από το
θάνατο τότε θα περιμέναμε να δούμε ότι αυτοί που πεθαίνουν και καταγράφονται σαν θάνατοι από Covid με ιστορικό εμβολιασμού είναι κάτω του 27,9% Σωστά;
• Πόσοι πέθαναν από Covid και είχαν ιστορικό εμβολιασμού; 22.
• Πόσοι πέθαναν συνολικά από covid από τη μέρα που αρχίσατε να αναφέρετε και το ιστορικό εμβολιασμού; 75.
• Πόσο είναι το ποσοστό αυτών που είχαν ιστορικό εμβολιασμού ανάμεσα στους δηλωμένους θανάτους από Covid; 22/75 = 29.3%.

Άρα πού είναι η προστασία από τον θάνατο που έχετε κουνήσει σαν δέλεαρ μπροστά στον κόσμο και το έχετε πράξει και δημόσια; Ακόμα περιμένουμε να τη δούμε."

Ας το πούμε και με άλλα λόγια: αναλύοντας τους αριθμούς ο επιστήμων επισημαίνει ότι η "προστασία" από τον θάνατο" που υποτίθεται θα μας χάριζαν τα εμβόλια είναι μόνο μια προπαγανδιστική παραίσθηση. Εάν τα εμβόλια παρείχαν προστασία από τον θάνατο, το ποσοστό των νεκρών ΕΜΒΟΛΙΑΣΘΕΝΤΩΝ θα έπρεπε να ήταν πιο μικρό. Αλλά είναι ακριβώς το ίδιο με το ποσοστό των εμβολιασθέντων: δηλαδή προστασία μηδέν.

Ο επιστήμων επίσης αναφέρεται στις προσπάθειες των Αρχών να "εξηγήσουν" πως τάχα οι εμβολιασθέντες πεθαίνουν επειδή είχαν πιο μεγάλες ηλικίες... τους κατακεραυνώνει με τα ίδια τους τα νούμερα:

"Μιλήσατε επίσης και για ηλικίες αυτών που πεθαναν και για τον επιβαρυντικό παράγοντα ηλικία. Είναι γελοίες πραγματικά οι προσπάθειες να ρίξετε τους θανάτους των εμβολιασμένων στο προχωρημένο της ηλικίας ενώ παράλληλα προσπαθείτε εδώ και βδομάδες να μας περάσετε το μήνυμα ότι δήθεν τώρα κατεβαίνει ο μέσος όρος της ηλικίας αυτών που πεθαίνουν επειδή και καλά έχετε προστατέψει τους υπερήλικες με το εμβόλιο.

Απλά μαθηματικά λοιπόν:
Μέσος όρος ατόμων που έχασαν τη ζωή τους από Covid και είχαν εμβολιαστεί: 78 έτη. ...Πόσος είναι ο μέσος όρος όλων όσων έχασαν τη ζωή τους από covid στην κύπρο. Μας το δηλώνετε στα ημερήσια δελτία τύπου. 78 έτη!

Άρα εγώ με τα λίγα μαθηματικά δημοτικού που ξέρω βλέπω ότι δεν υπάρχει διαφορά στο μέσο όρο ηλικίας μεταξύ αυτών που εμβολιαστηκαν και έχασαν τη ζωή τους και αυτών που δεν εμβολιάστηκαν και έχασαν τη ζωή τους."

Με άλλα λόγια, τα δεδομένα τεκμηριώνουν ΠΕΝΤΑΚΑΘΑΡΑ αυτό που γράφει ο Σώτος Χριστοδούλου: "ότι οι πιθανότητες ένας που εμβολιάστηκε να χάσει τη ζωή του από Covid είναι οι ίδιες με έναν που δεν εμβολιάστηκε."
Το κείμενο με τους επίσημους αριθμούς και την ανάλυση, δημοσιεύτηκε εδώ:
■ ΣΩΤΟΣ ΧΡΙΣΤΟΔΟΥΛΟΥ, Φαρμακοποιός
https://www.facebook.com/sotos.christodoulou.9/posts/10225229534916282 [3].

Τώρα βέβαια με την λήξη του θανατικού δεκαήμερου μπαίνουμε σε νέα φάση όπου τα πράγματα, επισφραγισμένα από τους θανάτους εμβολιασθέντων και μη, εξελίσσονται στη βάση της τραγικής πραγματικότητας που μας επιβλήθηκε:
🟣 Έχουν δυστυχώς ΗΔΗ πεθάνει τα πιο ευάλωτα μέλη της κοινωνίας - ως επί το πλείστον άτομα βεβαρυμένα με άλλες θανατηφόρες υποκείμενες ασθένειες και σε μεγάλες ηλικίες - οι δε θάνατοι που προκλήθηκαν είτε από τις υποκείμενες ασθένειες είτε από τα ίδια τα εμβόλια, φορτώθηκαν στον κορωνοϊο.
🟣 Το αποτέλεσμα είναι πως τα ετοιμοθάνατα ή και πολύ ευάλωτα άτομα ΤΩΡΑ είναι πολύ λιγότερα - και άρα οι θάνατοι ίσως θα αραιώσουν ή θα ελαττωθούν. Αυτό, οι δόλιες Ιατρικές-Κρατικές Αρχές και ΜΜΕ θα μας το παρουσιάσουν ως "νίκη του εμβολιασμού"!
🟣 Η ΑΠΑΓΟΡΕΥΣΗ των ανακοινώσεων ΘΑΝΑΤΩΝ ΤΩΝ ΕΜΒΟΛΙΑΣΜΕΝΩΝ με κορωνοϊό εύκολα συγκαλύπτει και την απόκρυψη θανάτων ΑΠΟ τους εμβολιασμούς. Η Επιστήμη έχει ήδη τεκμηριώσει για πολλά χρόνια τώρα τους βιολογικούς μηχανισμούς μέσω των οποίων τα εμβόλια για τους κορωνοϊούς και τα εμβόλια τύπου RNA προκαλούν ασθένειες, παράλυση και θάνατους, ΙΔΙΩΣ όταν ο εμβολιασθής μολυνθεί με τον ιό και προκύψει η αντίδραση ενός "φαλλαρισμένου" ανοσοποιητικού συστήματος που τραυματίστηκε από τον εμβολιασμό.

{Άν ενδιαφέρεστε για την επιστημονική τεκμηρίωση που αφορά επιδείνωση της ασθένειας κόβιντ μέχρι και θάνατο μετά από τον εμβολιασμό, παρακαλώ δείτε πιο κάτω στις Σημειώσεις. Εκεί παρατίθενται αυτούσιες οι πηγές από την επιστημονική βιβλιογραφία στην κοινή επιστημονική γλώσσα (αγγλικά) [4]. Επίσης, υπάρχει στα ελληνικά μια μακροσκελής ανάλυση και παρουσίαση των κειμένων από μένα στην ιστοσελίδα της γιατρού Αντωνίας Κυπριανού [5] - αυτή η παρουσίαση θα δημοσιευτεί ξανά και σε ενοποιημένη, ολοκληρωμένη μορφή σύντομα.}


🟢 Ανάλυση: Μέρος Β ~ Η μεθόδευση της απάτης και συγκάλυψης από Ιατρικές και Κρατικές Αρχές με την συμπραξία των ΜΜΕ/Τύπου

🟣 Είναι φανερό πως η απάτη για την κορωνοκρίση ΘΕΜΕΛΙΩΘΗΚΕ πάνω στην απαγόρευση των νεκροτομών για περισσότερο από ένα χρόνο τώρα στην Κύπρο, έτσι ώστε οι ιατροδικαστές και παθολογοανατόμοι να ΜΗΝ μπορούν να εξακριβώσουν με νεκροψία και ιστοπαθολογική εξέταση τα αίτια θανάτου αυτών που υποτίθεται "πέθαναν από κορωνοϊό". Πιο ειδικά, με αυτή την απαγόρευση διαιωνίζεται η απάτη έτσι ώστε να μην μπορούν να ταξινομηθούν ορθά οι θάνατοι ατόμων που πέθαναν από άλλες αιτίες και που ήταν απλώς "θετικά" στον κορωνοϊό κατά τον ουσιώδη χρόνο.

Στις ΗΠΑ, όπου τηρούνται καλύτερα αρχεία (ασχέτως του πως τα αξιοποιούν εκεί οι διεφθαρμένες Αρχές), το ανώτατο κρατικό Κέντρο Ελέγχου και Πρόληψης Ασθενειών (US CDC) δηλώνει καθαρά ότι μόνο 5% των νεκρών που καταγράφηκαν είχαν ΜΟΝΟ κορωνοϊό. Οι πλείστοι, το 95%, πέθαναν από φονικές ασθένειες που οι ασθενείς είχαν προηγουμένως - δηλαδή από τις λεγόμενες "υποκείμενες νόσους". Ο μέσος όρος αυτών των ασθενών υπέφερε ήδη από περίπου κατά μέσον όρο 4 άλλες φονικές ασθένειες έκαστος:
■ "For over 5% of these deaths, COVID-19 was the only cause mentioned on the death certificate. For deaths with conditions or causes in addition to COVID-19, on average, there were 4.0 additional conditions or causes per death." In other words 95% of the deaths were due to OTHER LETHAL conditions which existed at the same time as infection with SARS-COV-2.
https://www.cdc.gov/nchs/nvss/vsrr/covid_weekly/index.htm

🟣 Η απάτη διαιωνίζεται με την πρόσφατη απόφαση νέας φίμωσης, να σταματήσει να ανακοινώνεται το αν οι νεκροί με κορωνοϊό πέθαναν με "υποκείμενες νόσους" - πράγμα που στις πλείστες των περιπτώσεων σημαίνει πέθαναν ΑΠΟ τις υποκείμενες νόσους και όχι από κόβιντ.

"Σύμφωνα με την Εκπρόσωπο του Υπουργείου Υγείας, η απόφαση πάρθηκε μετά από σύσταση του Σύμβουλου του Υπουργείου για θέματα κοινωνιολογίας και ψυχολογίας στην πανδημία και μέλος της ΣΕΕ Κωνσταντίνου Φελλά.
[...]
Ο καθηγητής Κωνσταντίνος Φελλά ο οποίος εξήγησε ότι με την φράση 'υποκείμενα νοσήματα' αντιμετωπίζεται διαφορετικά ο θάνατος ενός ατόμου με covid, καθώς θεωρείται δεδομένο ότι ο πάσχων θα έχανε τη ζωή του αν όχι από κορωνοϊό, από κάποια άλλη ασθένεια."
■ 1 στους 3 που πέθαναν μεταξύ 24/3-9/5 είχε ιστορικό εμβολιασμού
https://simerini.sigmalive.com/article/2021/5/14/1-stous-3-pou-pethanan-metaxu-243-95-eikhe-istoriko-emboliasmou

🟣 Μετά από την θεμελίωση της απάτης στην απαγόρευση νεκροψίας, την διαιώνιση της απάτης με απαγόρευση της ανακοίνωσης "υποκείμενων νοσημάτων", τώρα η απάτη σφραγίζεται με μια νέα φίμωση: απαγορεύθηκε και η ανακοίνωση του αν οι νεκροί ήταν εμβολιασμένοι ή όχι. Με την συμπραξία των ΜΜΕ/Τύπου σε αυτή την ανίερη συγκάλυψη και απάτη που στηρίζει το καθεστωτικό αφήγημα, έχουμε πλήρη συσκότιση και μηδέν διαφάνεια.

Η νέα συγκάλυψη του εγκλήματος διασφαλίζει - όχι μόνο διευκολύνει - το να μην γίνεται γνωστό καθόλου πλέον όχι μόνο το πόσοι εμβολιασθέντες πεθαίνουν ενώ είναι "θετικοί" στον κορωνοϊό, αλλά και το πόσοι "θετικοί" εμβολιασθέντες πεθαίνουν από το εμβόλιο.

Η νέα συγκάλυψη έγινε με τον ισχυρισμό πως τάχα προστατεύονται τα προσωπικά δεδομένα των νεκρών. Η ίδια η Επίτροπος Προσωπικών Δεδομένων Ειρήνη Λοϊζίδου Νικολαϊδου, όμως, με δήλωση της φανέρωσε πως ο ισχυρισμός αυτός αποτελεί ανοησία και ψέμμα: η "Επίτροπος, τόνισε πως δεν αφορά θέματα που άπτονται των προσωπικών δεδομένων αλλά απόφαση του Υπουργείου Υγείας, καθότι τα νομικά πρόσωπα και οι αποβιώσαντες δεν έχουν προσωπικά δεδομένα, σημειώνοντας πως η απόφαση αυτή ενδεχομένως να αφορά άλλους λόγους." [6].

Επιπλέον, αρκετές εφημερίδες δημοσίευσαν δήλωση από το Υπουργείο Υγείας όπου εκφράζεται καθαρά το ότι η απόφαση για φίμωση και συσκότιση είναι "να μην δημιουργούνται αμφιβολίες για την αποτελεσματικότητα των εμβολίων και διστακτικότητα για το εμβολιαστικό πρόγραμμα" [7], [8]. Σχεδόν ΟΛΟΙ οι δημοσιογράφοι, συντάκτες, λειτουργοί Τύπου/ΜΜΕ αποδέκτηκαν αυτή τη νέα συγκάλυψη χωρίς διαμαρτυρία - θα μπορούσε να πει κάποιος πως ίσως και να ανακουφίστηκαν, γιατί τώρα θα είναι πολύ πιο δύσκολο να αποδεικτούν τα ψέμματα που δημοσιεύουν επί ένα χρόνο τώρα προωθώντας το καθεστωτικό αφήγημα.

🟣 Οι γνήσιοι και αφοσιωμένοι επιστήμονες όμως αγανακτούν με την νέα "στεγανοποίηση" της ροής ενημέρωσης και τον φόνο της διαφάνειας. Ο φαρμακοποιός Σώτος Χριστοδούλου σχολιάζοντας, έγραψε τα εξής:
"Εδώ που τα λέμε από πότε η στατιστική αναφορά σε δεδομένα και αριθμούς παραβιάζουν το ιατρικό απόρρητο; Ο κόσμος δεν έχει κανένα ενδιαφέρον να μάθει τις λεπτομέρειες του ατόμου που πέθανε χτές ή προχτές. Αλλά έχει κάθε έννομο ενδιαφέρον να ενημερώνεται για τις επιδημιολογικές παραμέτρους, ιδιαίτερα δε αν αυτές παίζουν σημαντικό ρόλο σε αποφάσεις που καλείται να πάρει και μάλιστα κάτω από φοβερή πίεση.

Το ποσοστό των ατόμων που έχουν εμβολιαστεί και νόσησαν είναι σημαντικό να γίνει γνωστό. Το ποσοστό από αυτούς που γίνονται εισαγωγή και έχουν εμβολιαστεί είναι επίσης σημαντικό. Το ποσοστό όσων έχουν πεθάνει με εμβολιασμό είναι άκρως σημαντικό. Αυτά είναι επιδημιολογικοί δείκτες που μπορεί να δώσουν πολύ χρήσιμες πληροφορίες στον κόσμο.

Και αν ο ισχυρισμός είναι ότι έχει σχέση ο χρόνος που μεσολάβησε από τον εμβολιασμό τότε να αναφέρονται στατιστικά ομαδοποιημένα τα αποτελέσματα. Αν δεν ξέρετε εσείς οι επιδημιολόγοι, στατιστικολόγοι, φωνάξετέ με να σας δείξω πως να το κάνετε.

Αν δεχτούμε τον ισχυρισμό σας ότι η δημοσιοποίηση αυτών των στοιχείων παραβιάζει το ιατρικό απόρρητο τότε δεν θα έπρεπε να γίνεται καμία απολύτως δημοσίευση σε κανένα επιστημονικό σύγγραμμα! Μα πόσο υπάνθρωποι τελικά νομίζετε κύριοι ότι είμαστε; Γουστάρετε αλήθεια θα 'θελα να 'ξερα αυτό τον σκοταδισμό;" [9].

🟣 Η συγκάλυψη της απάτης για τους νεκρούς και ασθενείς με τα νέα μέτρα φίμωσης έρχεται να προστεθεί στα προηγούμενα τεχνάσματα με τους αριθμούς όπου "κρούσματα", "θετικοί", "νεκροί ΜΕ κορωνοϊό" και "νεκροί ΑΠΟ κορωνοϊό" συγχέονται από το καθεστώς ΕΠΙΤΗΔΕΣ σε μια σαλάτα ώστε ο απλός άνθρωπος της καθημερινής ζωής να είναι υποτελής διαρκώς σ' ένα καθεστώς τρόμου, όπου κανένας αριθμός δεν έχει άλλο νόημα από το "τρέμε κόσμε!" Αναλύουμε - και ΑΠΛΟΠΟΙΟΥΜΕ - κάποια από αυτά τα θέματα, απομυθοποιώντας τα, εδώ:
🟢 Τι χάθηκε καθ' οδόν
🟢 Κορωνοϊός, Αριθμοί, Δευτερονόμιον
https://cyprusindymedia.blogspot.com/2020/12/blog-post.html
και εδώ:
🟢 Οι αριθμοί νεκρών, ασθενών, και μολυσματικών | Λογοκρισία από τον "Φιλελεύθερο"
https://cyprusindymedia.blogspot.com/2021/03/blog-post_25.html

Πέτρος Ευδόκας, petros@cyprus-org.net

ΣΗΜΕΙΩΣΕΙΣ

[1].
■ Τρεις νεκροί λόγω Covid-19 - Είχαν λάβει και τις δύο δόσεις
13 Μαΐου 2021, Mαριλένα Παναγή     
"...το προηγούμενο δεκαήμερο, στα νοσοκομεία άφησαν την τελευταία τους πνοή τρεις ηλικιωμένοι με πλήρες εμβολιαστικό ιστορικό.":
https://www.philenews.com/koinonia/eidiseis/article/1190136/pame-ga-triti-dosi-embolioy

[2].
■ Δύο νεκροί, ο ένας 47 ετών - Ανακοινώθηκαν άλλα 260 κρούσματα
12/05/2021 21:05
https://www.reporter.com.cy/local-news/article/809429

[3].
Για λόγους διαφάνειας και ενημέρωσης, και διότι υπάρχουν πολλά άτομα που δεν έχουν πρόσβαση στην σελίδα του Σώτου Χριστοδούλου στον ιστότοπο του Facebook, αναδημοσιεύουμε ολόκληρο το κείμενο του πιο κάτω, στο τέλος αυτού του άρθρου.

[4].
Οι πιο κάτω πηγές παρατίθενται και επεξηγούνται στα ελληνικά σε παρουσίαση μου στην Σημείωση με αριθμό [5], πιο κάτω.

■ Mechanisms of COVID-19 Vaccine Induced Injuries/Deaths
https://cyprusindymedia.blogspot.com/2021/05/mechanisms-of-covid-vaccine-induced.html

■ Vaccine-induced enhancement of viral infections
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7131326

■ New Side Effect From mRNA COVID Vaccines?
— Surprise finding in Israeli case series
https://www.medpagetoday.com/infectiousdisease/covid19vaccine/92106

■ UK gov’t. predicts ‘third wave’ of COVID deaths ‘dominated’ by those who are vaccinated
https://www.lifesitenews.com/news/uk-govt-predicts-third-wave-of-covid-deaths-dominated-by-those-who-are-vaccinated

■ Antibody-Dependent Enhancement of Viral Infections
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7119964

■ Antibody-dependent enhancement and SARS-CoV-2 vaccines and therapies
https://www.nature.com/articles/s41564-020-00789-5

■ mRNA-based SARS-CoV-2 vaccine candidate CVnCoV induces high levels of virus-neutralising antibodies and mediates protection in rodents
https://www.nature.com/articles/s41541-021-00311-w

■ The impact of COVID-19 vaccination campaigns accounting for antibody-dependent enhancement
https://www.biorxiv.org/content/10.1101/2021.01.04.425198v2.full

■ Does COVID-19 Vaccination Warrant the Classical Principle “ofelein i mi vlaptin”?
https://www.mdpi.com/1648-9144/57/3/253/pdf

[5].
Στη σελίδα της γιατρού Αντωνίας Κυπριανού:
https://www.facebook.com/antonia.kyprianou.5/posts/10215141093160342?comment_id=10215155819328487


[6].
■ Επίτροπος: Χωρίς προσωπικά δεδομένα οι θανόντες
https://www.philenews.com/koinonia/eidiseis/article/1193673/epitropos-choris-prosopika-dedomena-oi-thanontes

[7].
■ Κύπρος/Covid19:Δεν θα ανακοινώνονται αν τα θύματα είχαν εμβολιαστεί η όχι
https://www.sigmalive.com/news/local/781921/kyproscovid19den-tha-anakoinonontai-an-ta-thymata-eixan-emvoliastei-i-oxi

[8].
■ Υπ. Υγείας: Δεν θα ανακοινώνεται αν τα θύματα είχαν εμβολιαστεί ή όχι
https://www.kathimerini.com.cy/gr/kypros/kypros-ygeia/yp-ygeias-den-tha-anakoinwnetai-an-ta-thymata-eixan-emboliastei-i-oxi

[9].
Δημοσιεύτηκε ως σχόλιο, σκέλος διαλόγου στη σελίδα του Σόλωνα Αντάρτη:
"Από πότε η στατιστική αναφορά σε δεδομένα και αριθμούς παραβιάζουν το ιατρικό απόρρητο;"
https://www.facebook.com/solon.antartis/posts/10159236202956678

* * *

Σώτος Χριστοδούλου:
Για τους νεκρούς εμβολιασθέντες
3 Μαΐου, 2021

Σήμερα μάθαμε ότι οι 19 έγιναν 22. Ερώτηση: Προς τι αυτή η αγωνία ντε και καλά να πείσουμε τον κόσμο ότι όσοι φεύγουν μετά από εμβολιασμό φεύγουν επειδή έχουν επιβαρυντικούς παράγοντες ένω όσοι φεύγουν χωρίς εμβόλιο είναι απλά θάνατοι από Covid; Κατανοώ ότι υπάρχει μία κυβερνητική καμπάνια να στηρίξετε και θέλετε να πείσετε τον κόσμο να πάει να εμβολιαστεί. Ωραία. Δεν είναι ανάγκη να εκτίθεστε τόσο πολύ όμως. Μιλάτε με σωστά στοιχεία τουλάχιστον!
Αν λοιπόν χρησιμοποιήσουμε σαν κριτήριο επιτυχίας την πρόληψη θανάτων σε άτομα που εμβολιάστηκαν και εκτίθενται στον ιό τότε αυτό το κριτήριο δεν το έχουμε δει τουλάχιστον στην Κύπρο και τουλάχιστον μέχρι αυτή τη συγκεκριμένη χρονική στιγμή.

Σύμφωνα με τα στοιχεία του ECDC και τα στοιχεία που δημοσιεύετε στη σελίδα του pio έχουμε τα εξής στοιχεία:

Μέχρι στιγμής έχουν πάρει την πρώτη δόση εμβολίου το 27,9% του πληθυσμού και έχουν ολοκληρώσει το εμβολιαστικό σχήμα το 9.5% του πληθυσμού.
Αν λοιπόν το εμβόλιο παρέχει έστω και την παραμικρή προστασία από το θάνατο τότε θα περιμέναμε να δούμε ότι αυτοί που πεθαίνουν και καταγράφονται σαν θάνατοι από Covid με ιστορικό εμβολιασμού είναι κάτω του 27,9% Σωστά;
Πόσοι πέθαναν από Covid και είχαν ιστορικό εμβολιασμού; 22
Πόσοι πέθαναν συνολικά από covid από τη μέρα που αρχίσατε να αναφέρετε και το ιστορικό εμβολιασμού; 75
Πόσο είναι το ποσοστό αυτών που είχαν ιστορικό εμβολιασμού ανάμεσα στους δηλωμένους θανάτους από Covid; 22/75 = 29.3%

Άρα πού είναι η προστασία από τον θάνατο που έχετε κουνήσει σαν δέλεαρ μπροστά στον κόσμο και το έχετε πράξει και δημόσια; Ακόμα περιμένουμε να τη δούμε.

Μιλήσατε επίσης και για ηλικίες αυτών που πεθαναν και για τον επιβαρυντικό παράγοντα ηλικία. Είναι γελοίες πραγματικά οι προσπάθειες να ρίξετε τους θανάτους των εμβολιασμένων στο προχωρημένο της ηλικίας ενώ παράλληλα προσπαθείτε εδώ και βδομάδες να μας περάσετε το μήνυμα ότι δήθεν τώρα κατεβαίνει ο μέσος όρος της ηλικίας αυτών που πεθαίνουν επειδή και καλά έχετε προστατέψει τους υπερήλικες με το εμβόλιο;

Απλά μαθηματικά λοιπόν.

Μέσος όρος ατόμων που έχασαν τη ζωή τους από Covid και είχαν εμβολιαστεί: 78 έτη. (78,3  για την ακρίβεια - το έχω υπολογίσει).
Πόσος είναι ο μέσος όρος όλων όσων έχασαν τη ζωή τους από covid στην κύπρο. Μας το δηλώνετε στα ημερήσια δελτία τύπου. 78 έτη!

Άρα εγώ με τα λίγα μαθηματικά δημοτικού που ξέρω βλέπω ότι δεν υπάρχει διαφορά στο μέσο όρο ηλικίας μεταξύ αυτών που εμβολιαστηκαν και έχασαν τη ζωή τους και αυτών που δεν εμβολιάστηκαν και έχασαν τη ζωή τους.

Τελικά τα μειτ ιν σαιπρους δεδομένα μας λένε ότι οι πιθανότητες ένας που εμβολιάστηκε να χάσει τη ζωή του από Covid είναι οι ίδιες με έναν που δεν εμβολιάστηκε. Δεν υπάρχει καμία μετατόπιση της ηλικίας θανάτων σε άτομα που εμβολιάστηκαν. Αν επίσης υποθέσουμε ότι τα άτομα που εμβολιάζονται είναι συγκριτικά εκείνα τα οποία είναι περισσότερο προσεκτικά και συμπεριφέρονται κατάτι περισσότερο υπέυθυνα από το μέσο όρο το γεγονός ότι ανέμεσα στις απώλειες δεν βλέπουμε στατιστικά σημαντικές διαφορές ίσως μας βοηθήσει να καταρρίψουμε και το μύθο περί του "συμπεριφέρομαι υπεύθυνα άρα εμβολιάζομαι"

Εν κατακλείδι. Κόφτε το δούλεμα! Βρείτε άλλο μήνυμα στη διαφημιστική σας καμπάνια γιατί η προστασία από το θάνατο δεν πιάνει τόπο στην Κύπρο! Εκτίθεστε!

■ ΣΩΤΟΣ ΧΡΙΣΤΟΔΟΥΛΟΥ, Φαρμακοποιός

https://www.facebook.com/sotos.christodoulou.9/posts/10225229534916282

~~~~~~~~~~~~~~~~~

Η εικόνα εμφανίζεται καλύτερα με "κλικ!"


Thursday, 13 May 2021

Palestinian Refugees Deserve to Return Home. Jews Should Understand.

Continue reading the main story

An incredibly honest and politically surprising article published by the New York Times. (Below the article you can find the internet address of the original, and a printable version of it.)

Palestinian Refugees Deserve to Return Home. Jews Should Understand.

Palestinians from Gaza leaving the occupied West Bank to go to Jordan in 1968.
Credit...Agence France-Presse — Getty Images

Mr. Beinart, a contributing Opinion writer who focuses on politics and foreign policy, is an editor at large of Jewish Currents, where a version of this essay appeared.

Why has the impending eviction of six Palestinian families in East Jerusalem drawn Israelis and Palestinians into a conflict that appears to be spiraling toward yet another war? Because of a word that in the American Jewish community remains largely taboo: the Nakba.

The Nakba, or “catastrophe” in Arabic, need not refer only to the more than 700,000 Palestinians who were expelled or fled in terror during Israel’s founding. It can also evoke the many expulsions that have occurred since: the about 300,000 Palestinians whom Israel displaced when it conquered the West Bank and Gaza Strip in 1967; the roughly 250,000 Palestinians who could not return to the West Bank and Gaza after Israel revoked their residency rights between 1967 and 1994; the hundreds of Palestinians whose homes Israel demolished in 2020 alone. The East Jerusalem evictions are so combustible because they continue a pattern of expulsion that is as old as Israel itself.

Among Palestinians, Nakba is a household word. But for Jews — even many liberal Jews in Israel, America and around the world — the Nakba is hard to discuss because it is inextricably bound up with Israel’s creation. Without the mass expulsion of Palestinians in 1948, Zionist leaders would have had neither the land nor the large Jewish majority necessary to create a viable Jewish state. As I discuss at greater length in an essay for Jewish Currents from which this guest essay is adapted, acknowledging and beginning to remedy that expulsion — by allowing Palestinian refugees to return — requires imagining a different kind of country, where Palestinians are considered equal citizens, not a demographic threat.

To avoid this reckoning, the Israeli government and its American Jewish allies insist that Palestinian refugees abandon hope of returning to their homeland. This demand is drenched in irony, because no people in human history have clung as stubbornly to the dream of return as have Jews. Establishment Jewish leaders denounce the fact that Palestinians pass down their identity as refugees to their children and grandchildren. But Jews have passed down our identity as refugees for 2,000 years. In our holidays and liturgy we continually mourn our expulsion and express our yearning for return. “After being forcibly exiled from their land,” proclaims Israel’s Declaration of Independence, “the people kept faith with it throughout their Dispersion.” If keeping faith that exile can be overcome is sacred to Jews, how can we condemn Palestinians for doing the same thing?

Continue reading the main story

In addition to telling Palestinians they cannot go home because they have been away too long, Jewish leaders argue that return is impractical. But this too is deeply ironic because, as a refugee rights advocate, Lubnah Shomali, has pointed out, “If any state is an expert in receiving masses and masses of people and settling them in a very small territory, it’s Israel.” At the height of the Soviet exodus in the early 1990s, Israel took in about 500,000 immigrants. If millions of diaspora Jews began moving to Israel tomorrow, Jewish leaders would not say taking them in was logistically impossible. They would help Israel to do what it has done before: build large amounts of housing fast.

When most Jews imagine Palestinian refugees’ return, they probably don’t envision it looking like Israel’s absorption of Soviet Jews. More likely, they predict Palestinians expelling Jews from their homes. But the tragic reality is that not many Jews live in former Palestinian homes, since it is believed that only a few thousand remain intact. Ms. Shomali estimates that more than 70 percent of Palestinian villages that were destroyed in 1948 remain vacant. And the Palestinian activists and scholars who envision return generally argue that large-scale eviction is neither necessary, nor desirable. Asked in 2000 about Jews living in formerly Palestinian homes, the famed Palestinian literary critic Edward Said declared that he was “averse to the notion of people leaving their homes” and that “some humane and moderate solution should be found where the claims of the present and the claims of the past are addressed.”

None of this means refugee return would be simple or uncontested. Efforts at historical justice rarely are. But there is a reason the writer Ta-Nehisi Coates ends his famous essay on reparations for segregation and slavery with the subprime mortgage crisis that forced many Black Americans into foreclosure in the first decade of the 21st century. The crimes of the past, when left unaddressed, do not remain in the past. That’s also the lesson of the evictions that have set Israel-Palestine aflame. More than seven decades ago, Palestinians were expelled to create a Jewish state. Now they are being expelled to make Jerusalem a Jewish city. By refusing to face the Nakba of 1948, the Israeli government and its American Jewish allies ensure that the Nakba continues.

Perhaps American Jewish leaders fear that facing the crimes committed at Israel’s birth will leave Jews vulnerable. Once the Nakba taboo is lifted, Palestinians will feel emboldened to seek revenge. But more often than not, honestly confronting the past has the opposite effect.

After George Bisharat, a Palestinian-American law professor, wrote about the house in Jerusalem that his grandfather had built and been robbed of, a former Israeli soldier who had lived in it contacted him unexpectedly. “I am sorry, I was blind. What we did was wrong, but I participated in it and I cannot deny it,” the former soldier said when they met, and then added, “I owe your family three months’ rent.” Mr. Bisharat later wrote that he was inspired to match the Israeli’s humanity.

Continue reading the main story

“Just that response, writ large, is what awaits Israel if it could bring itself to apologize to the Palestinians,” he wrote. In that moment he saw “an untapped reservoir of Palestinian magnanimity and good will that could transform the relations between the two peoples.”

There is a Hebrew word for the behavior of that former soldier: “teshuvah.” It is generally translated as “repentance.” Ironically enough, however, its literal definition is “return.” In Jewish tradition, return need not be physical; it can also be ethical and spiritual. That means the return of Palestinian refugees — far from necessitating Jewish exile — could be a kind of return for us as well, a return to traditions of memory and justice that the Nakba has evicted from organized Jewish life.

“The occupier and myself — both of us suffer from exile,” the Palestinian poet Mahmoud Darwish once declared. “He is an exile in me and I am the victim of his exile.” The longer Jews deny the Nakba, the deeper our moral exile becomes. By facing it squarely and beginning a process of repair, both Jews and Palestinians, in different ways, can start to come home.

Peter Beinart (@PeterBeinart) is professor of journalism and political science at the Newmark School of Journalism at the City University of New York. He writes The Beinart Notebook, a weekly newsletter, and is editor at large of Jewish Currents, where a version of this essay appeared.

* * * 
Your own copy to save, or print:
http://cyprus-org.net/NYT.Palestinian.Refugees.Deserve.to.Return.Home.Jews.Should.Understand.pdf


* * *


Monday, 10 May 2021

Mechanisms of COVID-19 Vaccine Induced Injuries/Deaths

By Maggie Zhou, PhD (genetics)


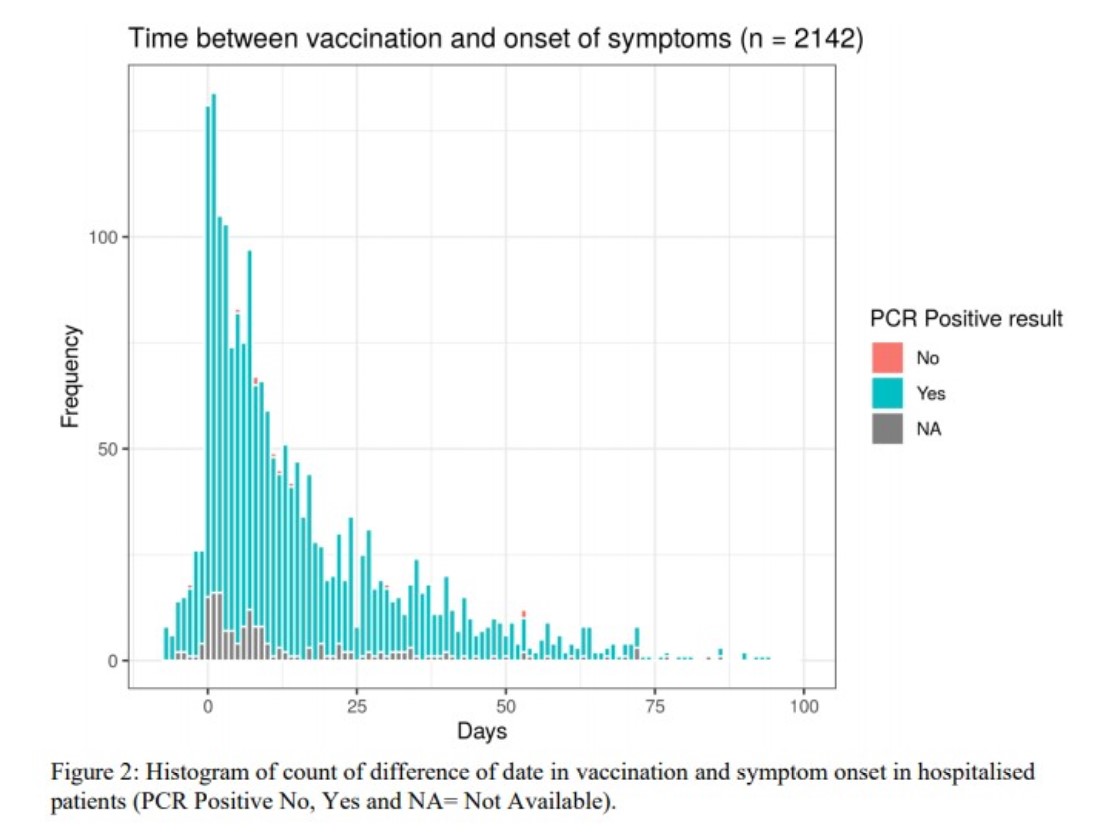
A study on UK government’s website, dated Apr 2021, conducted by the ISARIC4C consortium, found that among the hospitalized COVID patients who had ALREADY BEEN VACCINATED, the onset of symptoms is most commonly from the day of vaccination to 3 days after that.  The onset is 5x as frequent ON the day of the vaccination as the day BEFORE vaccination! [1]

The preferred mainstream explanation is blaming behavioural change – they assume that those who had been vaccinated shielded & isolated less.  Yet they have no evidence to back that up.  Crucially, “No one is suggesting there was a change of behaviour within care homes, except for inviting people in to carry out the vaccinations. However, care homes in every corner of the country saw outbreaks from December”, wrote a rebuttal published in the British Medical Journal.[2]

The other idea offered by some mainstream academics is that going to the vaccination centers itself may be a “super-spreader event” - but again, care homes didn’t fit that bill.

Also, even if these people did contract the virus on the vaccination day, why would more of them have symptom onset on that day and the 3 days immediately after, rather than the usual incubation period of 5 days?


FAR MORE LIKELY are the following mutually non-exclusive mechanisms:

1. The rebuttal in the BMJ mentioned above[2] pointed out that both Pfizer and AstraZeneca’s trials had shown white blood cell depletion in the first 3 days post vaccination.  The phenomenon is known for other vaccines as well, and there’s at least evidence in children that such transient white cell depletion results in susceptibility to viral infections.[3]  In this scenario, an infection previously kept in check by the immune system could become active when response to the vaccine depleted circulating white blood cells.

2. The mRNA and DNA vaccines use nanoparticles to enclose the nucleic acids.  There has been an accumulating number of studies that found that various types of nanoparticles can interfere with the function of our blood cells, and with the coagulation system, shifting the hemostatic balance, causing deep vein thrombosis (DVT) and disseminated intravascular coagulopathy (DIC), among other serious complications.[8,9]  Also, the mRNA vaccine nanoparticles contain PEG-lipid, and the the DNA vaccine nanoparticles contain polysorbate 80, both have been known to be allergenic and found responsible for anaphylactic reactions in the past.[10]

3. The spike protein of SARS-CoV-2 alone, introduced intratracheally, as well as in in vitro experiments, has been shown to damage lung vascular endothelial cells by downregulating ACE2, and consequently inhibiting mitochondrial function, triggering reactive oxygen species production, increasing glycolysis, and extracellular acidification.[11,4]

4. On Dec 9, 2020, BEFORE vaccination rollouts in most countries, Dr. J. Patrick Whelan MD PhD, formally warned the FDA that, according to multiple lines of evidence, vaccines using SARS-CoV-2 spike protein (including mRNA and DNA vector vaccines) may cause microvascular injury to distant organs including the brain, heart, liver, and kidneys.[5]

He cited evidence that while “the coronavirus replicates almost exclusively in the septal capillary endothelial cells of the lungs and the nasopharynx”, “viral lysis and immune destruction of those cells releases viral capsid proteins (or pseudovirions) that travel through the circulation and bind to ACE2 receptors in these other parts of the body…… that not only damages the microvascular endothelium but also induces the production of many pro-inflammatory cytokines”.  He cited evidence that the brain tissues of those that died from COVID were found to have pseudovirions (spike, envelope, and membrane proteins) without viral RNA, in the endothelia of cerebral microvessels, and that injecting just the S1 spike subunit in mice led to neurologic signs.[5]

5. On Jan 26, 2021, Dr. Hooman Noorchashm emailed the FDA regulators, Pfizer leaders and the press, to deliver “a warning and a, nearly certain, prognostication”, that anyone who has had a recent COVID infection (irrespective of whether they are symptomatic or convalescent) can be expected to have viral antigens in the endothelial lining of their blood vessels, and that vaccine triggered antigen specific immune response will target those antigens, and therefore those tissues, and cause tissue inflammation and damage.[6]  In other words, the vaccines will cause vasculature damage and blood clots in the lungs, as well as damage in the vasculature of the brain, heart, liver, kidney etc., anywhere residual viral antigens from a recent infection may be found.

It's relevant with regard to what Dr. Noorchashm is warning about, to note that Pfizer's clinical trial protocol (on page 41) explicitly excluded anyone who has had COVID-19 from enrolment.[7]

6. Another point specifically about the mRNA and DNA vaccines encoding the spike protein, is raised by Dr. Sucharit Bhakdi, who was for over 2 decades the head of the Institute of Medical Microbiology and Hygiene, University of Mainz, and Editor in Chief of Medical Microbiology and Immunology. 

He warned that a large part of the injected mRNA or DNA-containing nanoparticle packets encoding the spike protein will reach local lymph nodes, and through there, into blood circulation.  In the lymph nodes, when they’re taken up by lymphocytes which then express the spike protein, those cells will be targeted for destruction by other lymphocytes, (likely accounting for the white blood cell depletion mentioned in #1 above).  The lymphocytes thus activated will multiply and swarm out of the lymph nodes to seek out more S protein antigen.  They’ll attack any muscle cells where the S protein is presented (muscle swelling, pain).[12]

The nanoparticles that get into the bloodstream will be trapped there.  Some will fuse with blood cells, but most will be taken up by endothelial cell lining the smallest of veins where blood flows really slowly.  The expression and presentation of the S protein by these microvascular endothelial cells attracts and activates platelets, which induces clotting.  These cells also produce trash during spike protein production, which he says will be placed outside the cell, and attracts killer lymphocytes to attack the presenting endothelial cells, damaging the vascular lining, causing inflammation, and clotting.[12]

7. Many have been pointing out from the beginning, the very real danger of Antibody Dependent Enhancement of Disease (ADE), that any SARS-CoV-2 vaccine may cause.  All attempts to develop a vaccine against the closest human coronavirus, SARS-CoV, had failed in the past two decades, when vaccinated animal models got more severe disease and died, upon challenge with the actual virus.  All SARS-CoV-2 vaccines clinical trials have simply not had enough observation time to allow such a deadly consequence to become apparent, before the vaccine rollouts were rushed worldwide – and we’re already seeing the beginning of the onslaught! [13-15]

8. The SARS-CoV-2 spike protein has also been found to contain high sequence similarity to 4 human proteins essential for embryonic development, including Syncytin-1 and Syncytin-2, since February 2020.[16]  This lead Dr. Wolfgang Wodarg and Dr. Michael Yeadon (Pfizer's former chief scientific officer) to write an urgent petition on Dec 1, 2020, to the European Medicines Agency, to halt the vaccine rollout due to the possibility that antibodies against the S protein in vaccinated women may attack these proteins, preventing the formation of a placenta, and rendering them infertile.[17]  Like all the other warnings, it was completely ignored.

9. Yet another treachery with the spike protein is its potential ability to cause prion disease, both by the protein[45], and by the mRNA for it contained in Pfizer and Moderna vaccines[46]. Here’s a lengthy summery of these two papers.[47]

10. As if all that isn’t bad enough, some scientists (e.g., Dr. Judy Mikovits) have stated that vaccinated people may shed microRNAs (miRNA) derived from the genetic vaccines, which could explain the many adverse health effects that unvaccinated people around those vaccinated are reporting (especially many women reporting abnormal and extremely heavy menses, even spontaneous abortions).  She says these miRNAs can spread through air, and easily taken in by another person, which is part of our normal process of genetic material exchange with our environment.[18]

11. Here's yet another way that making our own cells express the spike protein via the genetic vaccines can lead to disaster: causing cells expressing the spike protein and cells that have ACE2 receptor on their surface to conglomerate, forming something called a "multinucleated syncytia":

"Proteins that mediate fusion between viral and cellular membranes can in some cases also do so between cells that express the viral fusion protein and those that express the viral receptor. For instance, cells expressing the HIV-1 envelope glycoprotein gp160 can form multinucleated syncytia with cells expressing the HIV-1 receptors CD4 and CCR5". The 2003 Nature paper went on to demonstrate that "293T cells transfected with ACE2, but not those transfected with human immunodeficiency virus-1 receptors, formed multinucleated syncytia with cells expressing S protein (of SARS-CoV-1)".[19]

12. A peer reviewed paper from MIT published in Apr 2021,[20] confirmed their earlier pre-print version published Dec13, 2020,[21] that “Reverse-transcribed SARS-CoV-2 RNA can integrate into the genome of cultured human cells and can be expressed in patient-derived tissues”.  Their results are “consistent with a LINE1 retrotransposon mediated, target-primed reverse transcription and retroposition mechanism.”  Even though with infection of SARS-CoV-2 virus, they detected only subgenomic sequences derived mainly from the 3′ end of the viral genome integrated into the DNA of the host cell, in the case of mRNA vaccines, given that we’re told the S protein gene is the only gene encoded by the mRNA, which by default is near the 3’ end, and was given a poly(A) tail and various other features to stabilize it, and given that tens of billions of copies of this mRNA are injected in one dose, it seems to me that there’s a good chance similar reverse transcription and retrotransposition of the S protein gene - the MOST PATHOGENIC gene of this entire virus - could really occur, as many scientists have warned from the beginning.  Once integrated into the genome, the host could express the S protein in the long term, which would trigger persistent autoimmune response, causing attack on the cells it has integrated into.

13. A paper published on May 20, 2021 found detectable levels of the spike protein in general circulation in 3 of 13 Moderna vaccine recipients, up to 29 days following the first dose.  The S1 subunit of the spike protein, previously found to be significantly associated with disease severity in COVID-19 patients, were found in general circulation in 11 of the 13 vaccine recipients, detectable up to 14 days after the first dose.[22]  This strongly supports many of the above hypothesized mechanisms of how the vaccine induced spike protein may cause harm.

14. I came across this wonderful, peer reviewed, comprehensive review article titled “Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19”.[23]  Two particularly disturbing things they discussed, among many, are:

- Vaccine shedding.  “…there is a plausible process by which it could occur through the release of exosomes from dendritic cells in the spleen containing misfolded spike proteins, in complex with other prion reconformed proteins. These exosomes can travel to distant places. It is not impossible to imagine that they are being released from the lungs and inhaled by a nearby person. Extracellular vesicles, including exosomes, have been detected in sputum, mucus, epithelial lining fluid, and bronchoalveolar lavage fluid in association with respiratory diseases (Lucchetti et al., 2021).”  They also discussed how, as the internet has recently discovered, that Pfizer’s clinical trial protocol implied that they anticipated the possibility of secondary exposure to the vaccine, and that they even suggested two levels of indirect exposure (i.e., if A is indirectly exposed to B who is indirectly exposed to C who has received the vaccine, the vaccine might actually affect A as well).

- An extremely disturbing scenario they described, is illustrated by the example of Bovine Viral Diarrhea (BVD).

They wrote: “A unique characteristic of BVD is that the virus can cross the placenta of an infected pregnant dam. This can result in the birth of a calf which carries intra-cellular viral particles which it mistakes as `self.’ Its immune system refuses to recognize the virus as a foreign invasion, and, as a result, the calf sheds the virus in large quantities throughout its life, potentially infecting the entire herd. It has become a widespread practice to identify such carrier calves and cull them from the herd in an attempt to curtail infection (Khodakaram-Tafti & Farjanikish, 2017).

“It seems plausible that a dangerous situation may arise in the future where a woman receives an mRNA vaccine for SARS-CoV-2 and then conceives a child shortly thereafter. The sperm would be free to take up RNA-embedded liposomes from the vaccine and convert them to DNA using LINE-1. They would then produce plasmids containing the code for the spike protein which would be taken up by the fertilized egg through the process described above. The infant that is born is then potentially unable to mount antibodies to the spike protein because their immune system considers it to be `self.’ Should that infant get infected with SARS-CoV-2 at any time in its lifespan, its immune system would not mount a defense against the virus, and the virus would presumably be free to multiply in the infant’s body without restraint. The infant would logically become a super-spreader in such a situation.”


SEVERAL MORE AUTOIMMUNE TYPE ADVERSE REACTION MECHANISMS:

15. According to Kanduc & Shoenfeld, originally published online in Apr 2020,[24] ‘Pulmonary surfactant plays a fundamental role in the physiology of ventilation by lowering the surface tension at the respiratory air-liquid interface within the alveoli. Excessively high values of surface tension would lead to alveolar collapse thus making ventilation and gas exchange impossible.’  Human surfactant proteins and associated regulators are extremely important for lung function.

They found that SARS-CoV-2 spike glycoprotein shares 24 pentapeptides (5 amino acid long segments, or 5-mers) with human surfactant proteins, out of which 13 were found in 52 SARS-CoV-derived immunoreactive epitopes in the database (epitopes are exposed parts of an antigen that get recognized by the immune system - so these 13 pentapeptides are known to be in immunogenic parts of SARS-CoV spike).  This is compared to 19 pentapeptides shared between human coronavirus HCoV-229E and the same collection of human surfactant proteins analyzed, out of which only 1 was found to be hosted in only one HCoV-derived epitope.  Immune cross-reaction against the body’s own surfactant proteins would explain why SARS-CoV-2 can cause so much more lung pathology compared to HCoV-229E which causes common cold and mild infections.

Amazingly, they also analyzed Pneumocystis carinii, a fungus responsible for aggressive and highly deadly Pneumocystis pneumonia in immune compromised patients, and found that it contains 17 of the 24 pentapeptides shared between SARS-CoV-2 and surfactant molecules!  Did the creators of SARS-CoV-2 bioweapon borrow some of these autoimmunogenic peptide elements from Pneumocystis carinii in hopes of beefing up the virus’ ability to impair respiratory function by causing an autoimmune attack on one’s own surfactant proteins?

Importantly, the authors warned against using vaccines based on entire SARS-CoV-2 antigens, which would in itself trigger autoimmune attacks.  THIS WAS IN APR 2020!  Yet, their advice was ignored by vaccine manufacturers and regulatory agencies, and the criminal vaccines were “developed” and unleashed upon the world’s population.

(In fact, even long before that, other researchers[25] have cautioned that before considering a protein as a vaccine antigen, special care should be taken in analyzing the sequence of tissue cross-reactive epitopes in order to avoid possible future side effects and autoimmune diseases.)

16. An article first published online in May 2020[26], found that 13 out of 50 human tissue antigens they tested cross reacted with a monoclonal antibody against the SARS-CoV-2 spike protein (Fig 1 of the article), and again warned against using the full length spike protein for vaccines.

17. A Sep 2020 article titled “Molecular mimicry between SARS-CoV-2 spike glycoprotein and mammalian proteomes: implications for the vaccine”[27], found that SARS-CoV-2 spike glycoprotein shares surprisingly many 6-mer and 7-mer peptides with humans, mice and to a lesser extent, rats, and not to other animals tested.  See Fig 1 in article.

They remarked: “A massive heptapeptide sharing exists between SARS-CoV-2 spike glycoprotein and human proteins. Such a peptide commonality is unexpected and highly improbable from a mathematical point of view…” “Likewise, the proteomes of the three human coronaviruses HKU1, 229E, and OC43, which were used as viral controls, have no or only a few peptides in common with the spike glycoprotein. In this regard, it seems that the SARS-CoV-2 spike glycoprotein is phenetically more similar to humans and mice than to its coronavirus “cousins”.”

“Finally, this study once more reiterates the concept that only vaccines based on minimal immune determinants unique to pathogens and absent in the human proteome might offer the possibility of safe and efficacious vaccines…” – a point resolutely ignored by the developers of ALL COVID-19 vaccines!

18. An April 2021 article titled “Divergent and self-reactive immune responses in the CNS [central nervous system] of COVID-19 patients with neurological symptoms”[28], found that cerebrospinal fluid (CSF)-derived monoclonal antibodies (mAbs) from an individual with COVID-19 target both viral and neural antigens, including one mAb that reacted to spike protein and neural tissue. CSF immunoglobulin G (IgG) from 5 of 7 patients with COVID-19 who had neurological symptoms showed antineural reactivity.  This study “suggests a role of autoimmunity in neurologic sequelae of COVID-19”, and yet again shows why using full-length spike sequence in vaccines is insane.

19. A July 2020 paper[29] proposed that it’s the binding of SARS-COV-2 spike protein with soluble ACE-2 (also called serum or plasma ACE-2, the ACE-2 enzyme ectodomain that has been cleaved from the cell surface, in a process called shedding, that occurs more frequently in hypertension and heart disease patients), that triggers autoimmune attacks on the ACE-2 (and possibly on related ACE), and the pulmonary vasculature damage because of dysregulation of the renin-angiotensin axis, as well as the subsequent severe course of disease and multi-organ attack in some COVID-19 patients.  The authors further developed their theory in a May 2021 paper[30], following additional related information that came to light recently.  Soluble ACE2 was found[31] to be the highest ranked predictor of total death or cardiometabolic diseases in general, and the serum of critically ill COVID-19 patients was recently found[32] to contain higher levels of soluble ACE-2.

If they’re right, then injecting the population with vaccines that put tens of billions of copies of the very protein that binds the plasma ACE-2 and could trigger autoimmune chain of events, would mean that the very people with high plasma ACE-2 levels and at higher risk of a severe COVID-19 infection, are being directly given the spike protein to trigger the very same reactions, bypassing the need for an infection!


MORE ON BLOOD CLOTS:

20. An article originally published in Apr 2021, in the New England Journal of Medicine, titled “Pathologic Antibodies to Platelet Factor 4 after ChAdOx1 nCoV-19 Vaccination”[33], linked blood clotting in AstraZeneca's COVID vaccine recipients to a pathologic immune reaction against Platelet Factor 4 (PF4).

The vaccine recipients presenting with thrombosis (blood clots) and thrombocytopenia (deficiency of platelets in the blood) syndrome showed “striking clinical similarities”[34] to heparin-induced thrombocytopenia (HIT), a known and serious complication that could result occasionally from the use of heparin (an anticoagulant that is also produced by the body) to treat or prevent thrombosis.  In the case of HIT, the use of heparin can trigger the generation of antibodies against heparin-PF4 complex.  In a subset of these patients, the binding of anti-PF4/heparin antibodies to platelet-associated PF4 produces receptor cross-linking, which strongly activates platelets, leading to blood clots.  A further subset of those patients presents clinical symptoms of thrombosis and thrombocytopenia.[35]

In the case of AstraZeneca vaccine recipients that suffered thrombosis/thrombocytopenia, 22 out of 23 (“mostly young, generally healthy”) patients tested positive for antibodies against PF4, suggesting a similar mechanism of autoimmune induced platelet activation that triggered blood clotting.[33]  Strikingly, “(a)ll the patients had d-dimer levels at presentation that were much higher than would be expected in patients with acute venous thromboembolism and are typically seen in patients with cancer.”

“The clinical features of this vaccine-induced syndrome are more typical of those seen in patients with HIT who have early reexposure to heparin, including severe thrombocytopenia, aggressive thrombosis, and disseminated intravascular coagulation.”

“Identification of the mechanism through which the vaccine could trigger the formation of these pathologic antibodies would require further study.”

21. In a June 11 interview[48] of Dr. Peter McCullough by Reiner Fuellmich, Dr. McCullough said the spike protein appears to cause a unique form of thrombosis, which is partly hemagglutination, where the spike protein attaches to sialic acid residues on red blood cells – normally RBC aren’t involved in coagulation, but here they are.  He also said that Italian doctors had shown that when the oxygen saturation goes down in the lungs, it was due to microthrombosis (micro-clotting) – in other words, it was micro-clotting in the blood vessels that lead to oxygen deficiency, not the impairment of lung function by viral infection as generally thought, in the patients that these Italian doctors observed.

In the same interview Dr. McCullough also mentioned that in some women, the breasts become so inflamed after the COVID-19 “vaccines”, that radiologists couldn’t read the mammogram, and Dr. McCullough’s hospital had to change mammography criteria to deal with that!


ANAPHYLACTIC REACTION TO POLYETHYLENE GLYCOL (PEG):

22. A December 2020 article in the journal Science[36], discussed how PEG, a component of the vaccine nanoparticles, could trigger anaphylactic reactions in some people:

‘As much as 72% of people have at least some antibodies against PEGs, according to a 2016 study led by Samuel Lai, a pharmaco-engineer at the University of North Carolina, Chapel Hill, presumably as a result of exposure to cosmetics and pharmaceuticals. About 7% have a level that may be high enough to predispose them to anaphylactic reactions, he found.’

‘In 1999, while working at the Walter Reed Army Institute of Research, Szebeni described a new type of drug-induced reaction he dubbed complement activation-related pseudoallergy (CARPA), a nonspecific immune response to nanoparticle-based medicines, often PEGylated, that are mistakenly recognized by the immune system as viruses.’

Full text of the Samuel Lai 2016 article: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6512330/


TREMORS, BEHAVIORAL & COGNITIVE ISSUES, AGGRESSION, ETC:

23. A twitter thread summed up some studies suggesting a possible mechanism how the Spike protein can cause neurodegenerative illnesses and behavioral/cognitive issues[37].

Monoamine oxidases (MAO-A and MAO-B) are enzymes that degrade neurotransmitters, such as serotonin, dopamine (DA), and norepinephrine (NE), maintaining a fine balance.  Through docking and molecular dynamic simulations, Hok et al found that the Spike Protein of SARS-CoV-2 binds to MAO Enzymes, with an affinity for MAO enzymes COMPARABLE to that for its ACE2 receptor.[38]  In other words, the spike protein creates an artificial EXCESS of these neurotransmitters (and a misbalance of them), by binding to the enzymes that would normally degrade them.

A 2006 study found that the immediate effects of known MAO inhibitors appear to be psychostimulant-like, as they substitute for the discriminative stimulus effects of cocaine.[39]

MAO inhibitors also increase serotonin. A 2019 NIH study found that increased extracellular serotonin in the ventral pallidum (VP) and orbitofrontal cortex (OFC) also may contribute to reward and may underlie cognitive deficits observed in users of cocaine.[40] (Can people get addicted to these “vaccines” after frequent shots?)

Evidence from preclinical and clinical studies support an association between monoamine oxidase-A brain levels and aggression.[41]

Histamine is also a monoamine, whose breakdown is inhibited by the downregulation of MAO. According to this page about histamine, “Monoamine Oxidase (MAO) is an enzyme that breaks down N-methylhistamine to N-methylimidazole acetic acid. SNPs in the gene that encodes for this enzyme can cause histamine levels to stay high rather than be degraded.”[42]  Interestingly, a paper in Inflammation Research said “Reports that the over-the-counter histamine H2 receptor antagonist famotidine could help treat …COVID-19… appeared from April 2020.”[43]


SUPPRESSION OF INNATE IMMUNE RESPONSE, DNA REPAIR ETC. BY THE “VACCINES”:

24. An excellent June 2022 paper with Dr. Peter A.McCullough as the senior author, titled “Innate immune suppression by SARS-CoV-2 mRNA vaccinations: The role of G-quadruplexes, exosomes, and MicroRNAs” reviews evidence and details the many mechanisms of how the COVID-19 “vaccines” are able to suppress innate immunity, and cause cancer, neurodegenerative diseases, and a host of other conditions.[44]

They cited a study on how the spike transfected cells release exosomes loaded with microRNAs (miRNA) that suppress USP33 and IRF9 levels in distant cells/tissues, while activating a range of pro-inflammatory gene transcripts.  IRF9 is a interferon regulatory factor, critical in interferon (IFN) mediated innate immunity.

They cited a Chinese study that found volunteers who received the inactivated whole SARS-CoV-2 “vaccine” had increased NF-κB signaling and reduced type I IFN responses 28 days after “vaccination”.

They cited studies that found the spike protein is able to both directly inhibit DNA repair in transfected cells (with implications on cancer, and adaptive immunity which is dependent on NHEJ recombination), and indirectly by changing the miRNA content of exosomes released by transfected cells, thereby inhibiting DNA repair mechanisms in distant cells and tissues that take up these exosomes.

They also showed how the methods used by mRNA “vaccine” designers to stabilize the spike mRNA, including the high GC content, and especially the potential Guanine quadruplexes (pG4s), may be the culprit in initiating prion-like aggregation and neurological disease onset, as well as in causing cancer; etc. etc.)


So indeed, the spike protein that the vaccines contain or encode for, is alone sufficient to cause COVID symptoms (and deaths in severe cases), and have numerous medium to long term potential serious consequences.  Only criminal governments would have rushed it ahead and imposed it on the world with utter deceit.


[1] https://lockdownsceptics.org/2021/05/01/major-study-finds-abundance-of-patients-admitted-to-hospital-with-covid-within-seven-days-of-vaccination/

https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/982499/S1208_CO-CIN_report_on_impact_of_vaccination_Apr_21.pdf

[2] https://www.bmj.com/content/372/bmj.n783/rr

[3] https://pubmed.ncbi.nlm.nih.gov/29525279/

[4] https://medicalxpress.com/news/2021-04-sars-cov-spike-protein-lung.html

https://www.eventscribe.net/2021/EB2021/index.asp?presTarget=1644160

[5] https://www.regulations.gov/document/FDA-2020-N-1898-0246

[6] https://www.lifesitenews.com/opinion/cardiothoracic-surgeon-warns-fda-pfizer-on-immunological-danger-of-covid-vaccines-in-recently-convalescent-and-asymptomatic-carriers

[7]https://media.tghn.org/medialibrary/2020/11/C4591001_Clinical_Protocol_Nov2020_Pfizer_BioNTech.pdf

[8] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6829615/

[9] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6289228/

[10] https://www.nejm.org/doi/full/10.1056/NEJMra2035343

[11] https://www.ahajournals.org/doi/10.1161/CIRCRESAHA.121.318902

[12] https://www.goldegg-verlag.com/goldegg-verlag/wp-content/uploads/corona_unmasked_engl_leseprobe.pdf

Video interview: https://beforeitsnews.com/u-s-politics/2021/04/german-microbiologist-to-reduce-the-worlds-populationthey-are-killing-people-with-these-covid-vaccines-video-2582255.html

[13] https://journals.plos.org/plosone/article?id=10.1371%2Fjournal.pone.0035421

[14] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3209347/

[15] https://www.bulatlat.com/2020/08/21/hazards-of-the-covid-19-vaccine/

[16] https://virological.org/t/response-to-ncov2019-against-backdrop-of-endogenous-retroviruses/396

[17] https://2020news.de/wp-content/uploads/2020/12/Wodarg_Yeadon_EMA_Petition_Pfizer_Trial_FINAL_01DEC2020_EN_unsigned_with_Exhibits.pdf

[18] https://jermwarfare.com/blog/judy-mikovits-viruses

[19] https://www.nature.com/articles/nature02145

[20] https://www.pnas.org/content/pnas/118/21/e2105968118.full.pdf

[21] https://21a86421-c3e0-461b-83c2-cfe4628dfadc.filesusr.com/ugd/659775_265cb97bf3bc4d25927f8c074ca6b51d.pdf

[22] https://academic.oup.com/cid/advance-article/doi/10.1093/cid/ciab465/6279075

[23] https://ijvtpr.com/index.php/IJVTPR/article/view/23

[24] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7165084/

[25] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6141484/

[26] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7246018/

[27] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7499017/

[28] https://www.cell.com/cell-reports-medicine/fulltext/S2666-3791(21)00116-6

[29] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7351250/

[30] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8021777/

[31] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7529405/

[32] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7848790/

[33] https://www.nejm.org/doi/full/10.1056/NEJMoa2105385

[34] https://www.hematology.org/covid-19/vaccine-induced-immune-thrombotic-thrombocytopenia

[35] https://ashpublications.org/blood/article/112/7/2607/24708/Heparin-induced-thrombocytopenia-a-historical

[36] https://www.sciencemag.org/news/2020/12/suspicions-grow-nanoparticles-pfizer-s-covid-19-vaccine-trigger-rare-allergic-reactions

[37] https://twitter.com/Parsifaler/status/1452099036077608963

[38] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8868002/

[39]https://www.researchgate.net/publication/7281141_Effects_of_Monoamine_Oxidase_Inhibitors_on_Cocaine_Discrimination_in_Rats

[40] https://nida.nih.gov/news-events/nida-notes/2019/02/disruption-serotonin-contributes-to-cocaines-effects

[41] https://rarediseases.info.nih.gov/diseases/3531/monoamine-oxidase-a-deficiency

[42] https://healinghistamine.com/blog/genetics-histamine-intolerance/

[43] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7673069/

[44] https://www.sciencedirect.com/science/article/pii/S027869152200206X

[45] https://www.mdpi.com/2076-2607/10/2/280

[46] https://scivisionpub.com/pdfs/covid19-rna-based-vaccines-and-the-risk-of-prion-disease-1503.pdf

[47]https://www.facebook.com/maggie.zhou.543/posts/pfbid0yPpaVdRVBQsV5vyDEmQLefB41k2BnGNu38Zz3GZs5ZMfhbW68gNS6BzSCTpMnAgyl

[48] Video titled “DR. PETER MCCULLOUGH ON WITH REINER FUELMICH JUNE 11, 2021” https://www.bitchute.com/video/rKP61hruGxIt/


~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~

Maggie Zhou received her PhD in genetics from the University of Wisconsin - Madison in 1997, and worked as a computational biologist for a number of years.  She is currently an independent seeker of truth.

~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~